
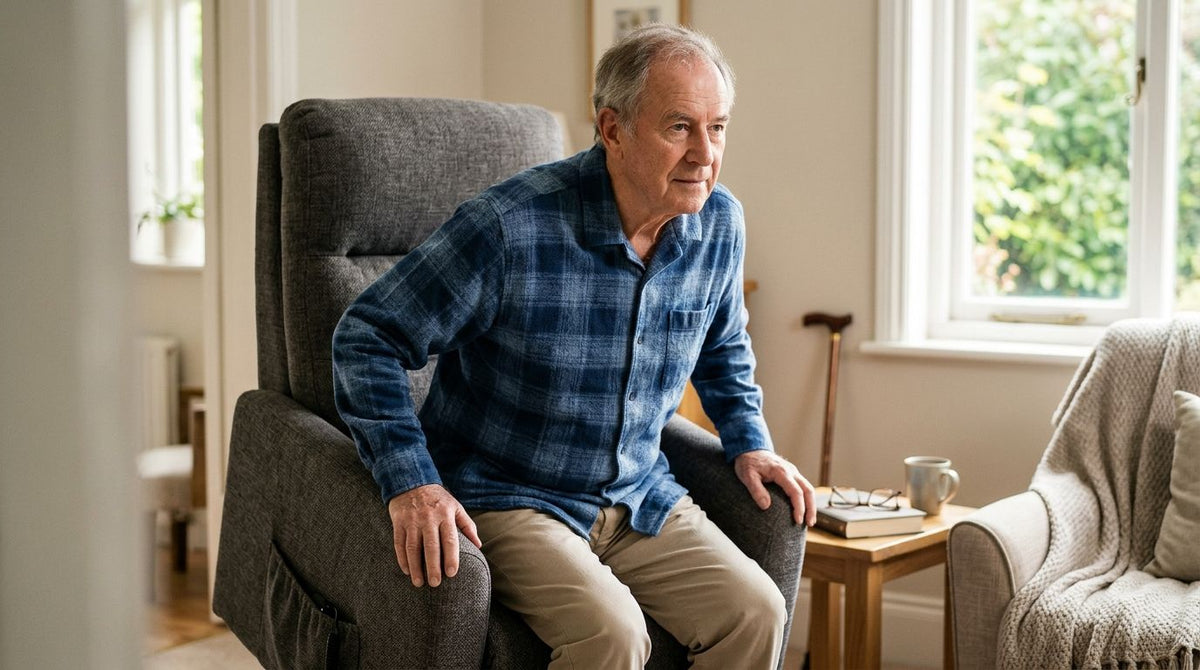
Lift chairs for Parkinson's disease patients solve one problem above all others: getting from seated to standing without a freezing episode, a stumble, or a caregiver forcing the transfer. The powered lift mechanism replaces the pushing, rocking, and momentum a healthy adult uses to stand, which matters because Parkinson's rigidity and postural instability make that push-off unreliable at almost any disease stage.
This segment's needs diverge sharply from a general recliner buyer's: tremor affects fine motor control of buttons, orthostatic hypotension makes fast position changes dangerous, and freezing of gait means the chair has to deliver the user to a stable standing position, not just tilt them forward and hope.
- Lift chairs for Parkinson's disease patients need slow, controlled rise speed to prevent orthostatic hypotension drops in blood pressure.
- Infinite-position lift chairs with a wall-hugger base suit mid-to-late Hoehn and Yahr stages better than 2-position models.
- Large, high-contrast, single-button remotes reduce control errors caused by tremor and reduced dexterity.
- Seat height of 19 to 21 inches at full lift lowers fall risk during the stand-to-walk transition.
- Heat and massage settings are a comfort add-on, not a substitute for a properly sized lift mechanism.
Why lift chairs matter for Parkinson's disease patients
Parkinson's disease is staged clinically on the Hoehn and Yahr scale, running from stage 1 (mild, one-sided symptoms) to stage 5 (wheelchair-bound or bedbound without assistance). A lift chair bought at stage 1 or 2 usually needs different features than one bought at stage 3 or 4, which is the single biggest planning mistake families make.
The chair's job changes with the stage. Early on, it's about reducing strain during dozens of daily sit-to-stand cycles. Later, it's about preventing falls during the single most dangerous transfer of the day. Lift chairs for assisted living facilities cover the same lift-assist mechanics at a facility scale, and the sizing logic carries over directly to a home purchase.
Orthostatic hypotension — a blood pressure drop on standing — affects a meaningful share of Parkinson's patients, especially those on dopaminergic medication. A lift chair that snaps upright in 3 to 4 seconds can trigger dizziness or a fall on standing; one that takes 8 to 12 seconds to complete the lift gives the cardiovascular system time to adjust.
How to choose a lift chair for Parkinson's disease patients in 2026
Assess the Hoehn and Yahr stage before shopping
Don't buy on comfort alone — buy for the stage the patient is in now and the stage they'll likely reach within a year or two, since lift chairs aren't cheap to replace annually.
- Stage 1-2: focus on seat height and a firm-but-comfortable cushion, since independent transfers are still the norm
- Stage 3: add slow-lift settings and a wider base for balance during the stand
- Stage 4-5: prioritize infinite recline (near-flat) positions and caregiver-assist features
- Ask the treating neurologist or physical therapist for a stage estimate if it isn't already documented
- Re-evaluate the fit every 6 to 12 months as symptoms progress
Set the seat height and depth correctly
Seat-to-floor height at full lift needs to land the patient's feet flat on the floor with knees at roughly 90 degrees, which is the stable base every physical therapist trains patients to stand from.
- Measure the patient's lower leg length (floor to back of knee) before ordering
- Target a lifted seat height of 19 to 21 inches for most adults
- Choose a shallower seat depth (18-20 inches) for shorter or petite frames — see lift chairs for petite and small frame adults for sizing specifics
- Avoid deep, plush seats that let the body sink and shorten effective leg length at lift-off
Prioritize slow, controlled lift speed
A chair that lifts too fast defeats the purpose for patients managing orthostatic hypotension.
- Look for models with adjustable or inherently slow (8-12 second) lift cycles
- Avoid budget single-speed motors that complete the full recline-to-stand arc in under 5 seconds
- Test the chair in person if possible before ordering, since spec sheets rarely list lift duration
- Ask about a pause or hold button that stops the chair mid-lift if dizziness starts
Choose tremor-friendly controls
Standard recliner remotes with small, closely spaced buttons are hard to operate with hand tremor or reduced dexterity, which is one of the most common return reasons in this segment.
- Pick large, widely spaced, tactile buttons over touchscreen or membrane pads
- Favor remotes with raised icons the patient can identify by feel, not just sight
- A hardwired remote (not Bluetooth) removes pairing and battery-drain complications
- Test whether the control clips to the armrest, since a loose remote gets lost in cushions and forces an unsafe reach
Match recline range to mobility level
A 2-position chair (upright and slight recline) suits an independent stage 1-2 patient. An infinite-position or zero-gravity chair that reclines near-flat matters far more once daytime rest periods become part of the routine.
- Infinite-position lift chairs let the patient find a pressure-relieving angle for edema or stiffness
- Zero-gravity settings reduce lower-back load during long sitting periods — compare options in zero-gravity recliners
- Dual-motor chairs let the back and footrest move independently, useful when swelling needs elevation separate from recline angle
- Skip lay-flat chairs only if the patient sleeps in a separate bed and never naps in the chair
Check weight capacity and base stability
A wide, low base matters more for Parkinson's patients than for most other lift chair buyers, since postural sway during the stand-to-walk handoff is common.
- Confirm the rated weight capacity covers the patient with 20-30 lbs of margin, not the exact body weight
- Look at lift chairs ranked by weight capacity if the patient is at the higher end of standard ratings
- Choose a wall-hugger base only if the room allows the chair to sit within 4-6 inches of the wall and still fully recline
- Avoid narrow-footprint chairs marketed for small apartments unless space genuinely requires the tradeoff
Plan for caregiver assistance
Most Parkinson's patients eventually need a caregiver present for transfers, even with a lift chair doing the mechanical work.
- Position the chair so a caregiver can stand beside, not just in front of, the lift path
- Add a battery backup option so a power outage doesn't strand the patient mid-lift — see lift chairs with battery backup
- Keep a phone or call button within reach of the seated position, not just the standing position
- Coordinate with a home health aide or family caregiver on the specific lift sequence the patient responds to best
Lift chair options for Parkinson's disease patients compared
| Option | Best for | Key limitation |
|---|---|---|
| 2-position lift chair | Stage 1-2 patients still fully independent | No near-flat recline for extended rest periods |
| Infinite-position lift chair | Stage 3-4 patients needing variable recline | Larger footprint, higher cost than 2-position models |
| Zero-gravity lift chair | Patients with edema or lower-back pain alongside Parkinson's | Zero-gravity angle isn't a stable standing base on its own |
| Dual-motor lift chair | Patients needing independent back and footrest control | More buttons on the remote, which can complicate tremor control |
| Heavy-duty lift chair | Patients above standard 300 lb weight ratings | Larger, heavier chair that's harder to reposition in small rooms |
The clearest verdict: an infinite-position lift chair with an 8-12 second lift cycle and a large-button hardwired remote is the safest default for most Parkinson's disease patients past stage 2, and a 2-position model is enough for stage 1 patients who are still standing independently most of the day.
Common mistakes families make buying lift chairs for Parkinson's disease patients
- Buying for today's stage only. A 2-position chair bought at stage 2 often gets replaced within 18-24 months as recline needs change — buy one stage ahead when budget allows.
- Ignoring lift speed entirely. Retailers rarely list it, but a fast lift is a real fall and dizziness risk for anyone managing orthostatic hypotension.
- Choosing a touchscreen remote for style. It looks modern and fails the tremor test within weeks.
- Skipping the in-home measurement. Seat height and depth matter more than fabric or color, and a chair that's 2 inches too tall undermines the entire stand-to-walk sequence.
- Forgetting caregiver clearance. A wall-hugger base that saves 6 inches of room can block the exact spot a caregiver needs to stand during transfers.
FAQ
What is the best type of lift chair for Parkinson's disease patients?
An infinite-position lift chair with a slow, 8-12 second lift cycle and large-button hardwired remote is the best fit for most Parkinson's disease patients past Hoehn and Yahr stage 2. Stage 1-2 patients who are still standing independently often do fine with a simpler 2-position chair.
Why does lift speed matter for Parkinson's disease patients?
A fast lift cycle can trigger orthostatic hypotension, a blood pressure drop common in Parkinson's patients on dopaminergic medication, causing dizziness or a fall right at standing. A slower 8-12 second cycle gives blood pressure time to stabilize before the patient bears full weight.
Are zero-gravity lift chairs good for Parkinson's disease?
Zero-gravity lift chairs help with edema and lower-back pain that often accompany Parkinson's, but the zero-gravity angle isn't a stable position to stand from. Use zero-gravity as a rest setting and rely on the chair's standard lift-to-stand cycle for transfers.
What seat height is best for a Parkinson's patient's lift chair?
A lifted seat height of 19 to 21 inches puts most adults' feet flat on the floor with knees near 90 degrees, the stable base physical therapists train stand-to-walk transitions from. Measure floor-to-knee length before ordering rather than relying on standard sizing.
Do Parkinson's patients need a chair with tremor-friendly controls?
Yes — standard recliner remotes with small, closely spaced buttons are hard to operate with hand tremor or reduced dexterity. Large, tactile, hardwired buttons with raised icons reduce control errors significantly compared to touchscreen or membrane remotes.
How often should a Parkinson's patient's lift chair be reassessed?
Reassess fit and features every 6 to 12 months, since Parkinson's symptoms and Hoehn and Yahr stage progression change what the chair needs to do. A chair sized for stage 2 independence often needs an upgrade to infinite-position recline by stage 3 or 4.
Is a battery backup necessary on a Parkinson's patient's lift chair?
A battery backup matters most for patients who rely on the chair for every transfer, since a power outage during a lift cycle can strand them mid-motion. It's a smaller cost than the risk of an unsafe manual transfer during an outage.
One last thing
The feature that gets overlooked most in this segment isn't recline range or motor count — it's the pause function. A lift chair that lets the patient stop mid-cycle and hold that position gives them (and a caregiver) a built-in buffer against the dizziness spike that orthostatic hypotension causes right at the standing point, and very few buyers even ask about it before purchase in 2026.